
Rosacea
Types of Rosacea
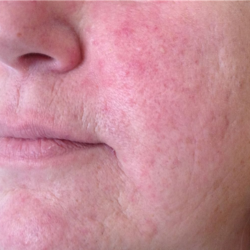
Erythematotelangiectatic Rosacea (ETR)
Erythematotelangiectatic rosacea is the most common and often the earliest form of rosacea. It is characterized by frequent flushing and persistent redness of the central face, especially the cheeks, nose, forehead, and chin. Over time, tiny visible blood vessels (telangiectasia) may appear, giving the skin a constant sunburn-like look.
People with ETR often experience burning, stinging, warmth, or skin sensitivity, and their skin may react easily to skincare products or environmental changes. Common triggers include sun exposure, heat, alcohol, spicy foods, stress, and temperature extremes. Without treatment, redness can become more persistent and spread over a larger area. Early management focuses on trigger avoidance, gentle skincare, barrier repair, and treatments such as topical medications and laser or light-based therapies to reduce redness and visible vessels.
Papulopustular Rosacea
Papulopustular rosacea is sometimes referred to as “acne rosacea” because it causes red bumps and pus-filled pimples that resemble acne. However, unlike acne, this type does not produce blackheads or whiteheads. Breakouts usually occur on the central face and are often accompanied by background redness, swelling, and skin sensitivity.
This form reflects active inflammation and may flare in cycles, with periods of worsening and improvement. Triggers are similar to other rosacea types and include heat, sun, stress, alcohol, and certain foods. Because it is inflammatory, papulopustular rosacea often requires medical treatment, such as topical anti-inflammatory medications and, in some cases, oral therapies. With appropriate treatment, flare-ups can be controlled and long-term skin damage reduced.
Red, acne-like bumps and pus-filled pimples with facial swelling and sensitivity—often mistaken for acne, but without blackheads.
Granulomatous Rosacea and Demodex-Related Rosacea
What does it look like?
This form presents as firm, smooth bumps or small nodules that may appear red-brown or yellow-brown. Facial redness and flushing are often minimal. The bumps are usually uniform and most commonly affect the cheeks, around the mouth, and around the eyes, which can make it resemble other skin conditions.
Why does it occur?
Granulomatous rosacea is thought to be related to abnormal immune activity in the skin. In some patients, inflammation may be triggered by microorganisms such as Demodex mites or certain bacteria.
How is it treated?
Granulomatous rosacea often requires oral treatment rather than topical creams alone. Therapy may include low-dose anti-inflammatory medications such as doxycycline, and in more persistent cases, low-dose isotretinoin. With appropriate treatment, symptoms can be effectively controlled. The good news: Rosacea is manageable. With the right combination of medical care, skincare, and advanced treatments such as prescription therapies and laser technology, symptoms can be significantly improved and flare-ups reduced.
Phymatous Rosacea
Phymatous rosacea is a more advanced subtype of rosacea that causes gradual thickening and enlargement of the skin. It most commonly affects the nose (called rhinophyma), but can also involve the chin, forehead, ears, or eyelids. This form develops slowly over time and is seen more often in men.
What causes it?
Phymatous rosacea is linked to long-standing inflammation, abnormal blood vessel changes, overgrowth of oil (sebaceous) glands, and possibly Demodex mites.
What does it look like?
Skin becomes thickened, bumpy, and uneven, with enlarged pores and an oily texture. Without treatment, visible skin distortion can occur.
How is it treated?
Once thickening develops, creams or pills alone are usually not enough. Treatment often involves laser therapy, radiofrequency or electrosurgery, or surgical contouring to restore normal skin shape. Medical treatments may help slow progression, but procedures are often needed to correct existing changes.
Why early treatment matters
Rosacea is progressive. Treating it early—before thickening or scarring occurs—can help preserve normal skin appearance and prevent permanent changes.
Ocular Rosacea
Red, irritated, watery eyes with a burning or gritty sensation, eyelid inflammation, or frequent styes—sometimes occurring even without obvious skin redness.
Firm yellow-brown or red bumps on the cheeks and around the eyes, sometimes linked to Demodex mites that normally live on the skin but can trigger inflammation in some patients.
Ocular rosacea is a form of rosacea that affects the eyes and eyelids, causing chronic irritation and inflammation. It may occur with or without visible facial rosacea and can involve the cornea in more severe cases. More than half of people with rosacea experience eye symptoms, which may appear before skin changes, most commonly between ages 30–60.
It is caused by fragile blood vessels, blocked eyelid oil glands (meibomian gland dysfunction), immune imbalance, and overgrowth of Demodex mites. Triggers include sun exposure, heat, alcohol, spicy foods, and stress.
Symptoms include red, dry, gritty, or burning eyes, tearing, light sensitivity, eye fatigue, and sometimes blurred vision. Exam findings may show inflamed eyelids, blocked oil glands, crusting, frequent styes, and persistent redness.
Treatment focuses on improving eyelid health and reducing inflammation with lid hygiene, artificial tears, and medications such as doxycycline.
Advanced options include IPL or LipiFlow, prescription anti-inflammatory drops like cyclosporine, and specialized care if the cornea is affected.
Lifestyle measures—such as sun protection, an anti-inflammatory diet, and gut health support—help reduce flares and protect long-term eye health.
Rosacea Stages — At a Glance
Rosacea is a chronic, progressive skin condition, but not everyone moves through every stage.
Early recognition and treatment can significantly slow progression and reduce flares.
Stage 1
Flushing & Sensitivity
The skin flushes easily and may feel warm, burning, or stinging, often appearing normal between flares. This stage is driven by over-reactive blood vessels. Common triggers include heat, sun exposure, alcohol, stress, and spicy foods. Management focuses on trigger avoidance, calming inflammation, and strengthening the skin barrier.
Stage 2
Persistent Redness
Redness becomes more constant, especially on the central face, and tiny visible blood vessels (telangiectasias) may appear. Skin sensitivity increases over time. Treatment often includes medical-grade skincare, topical therapies, antioxidants, and vascular laser or light treatments to reduce redness.
Stage 3
Inflammatory Rosacea
Inflammation intensifies, leading to red bumps, swelling, and pus-filled pimples that are often mistaken for acne. This stage typically requires targeted anti-inflammatory treatments, topical or oral medications, and attention to skin and gut health.
Stage 4
Skin Thickening (Phymatous Rosacea)
The skin gradually becomes thickened, uneven, and bumpy with enlarged pores—most commonly affecting the nose (rhinophyma). This stage is more common in men and may require advanced laser or surgical treatments to restore normal skin contour.

